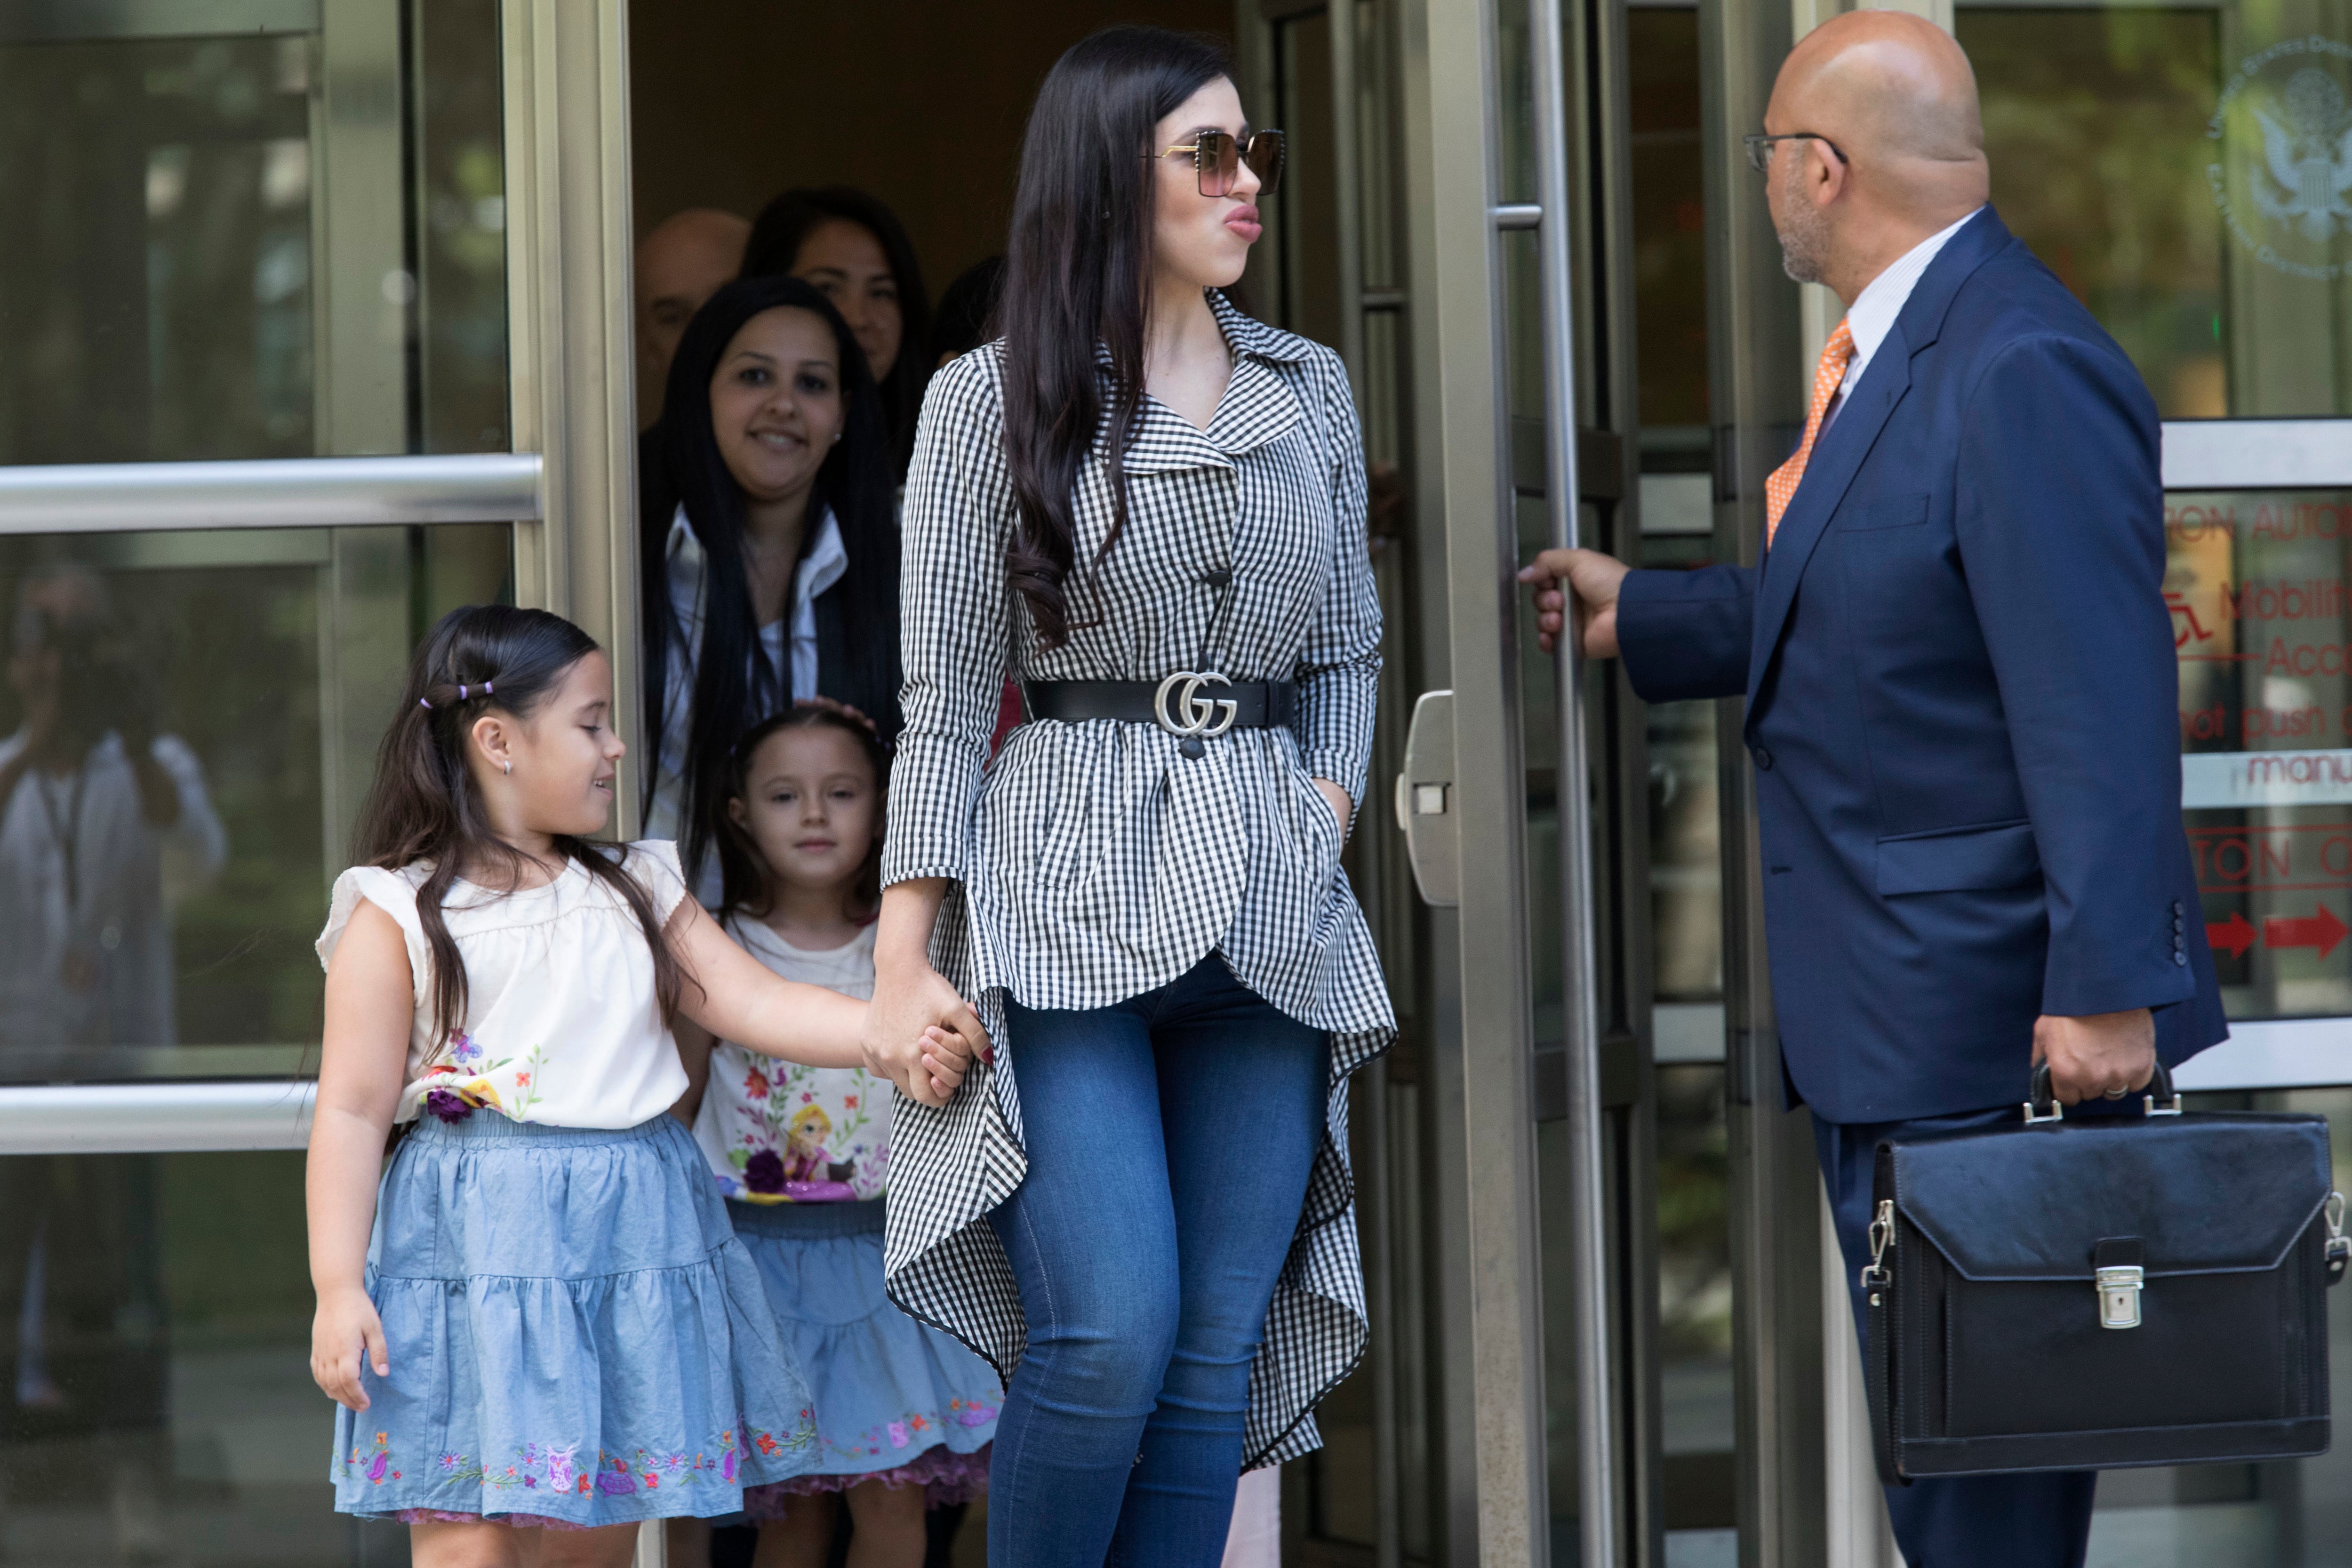❌

Reading view

Rep. Steve Cohen Thinks the DEA Shouldn't Be Practicing Medicine

A man wearing glasses and a suit & tie speaks into a small microphone with a placard in front of him that says "Mr. Cohen." | Photo: Michael Brochstein/Sipa USA/Newscom

For more than half a century, federal officials have classified drugs into legal categories that determine who can manufacture, prescribe, or study them, and who goes to prison for possessing or selling them. Those classifications carry enormous consequences. They also reflect decades of political pressure, moralization, myth, and stigma.

Rep. Steve Cohen (D–Tenn.) proposes to change that. His Public Health and Research Reforms in Controlled Substances Act of 2026 would substantially overhaul federal drug scheduling, shift key decisions from law enforcement to health officials, ease research restrictions, deschedule marijuana, and reduce mandatory prison penalties.

While the proposal preserves too much of the drug prohibition infrastructure, it represents a major step toward a more rational, evidence-based, and humane drug policy.

The Controlled Substances Act currently combines judgments about a drug's potential for abuse with judgments about its medical usefulness. Congress vested scheduling authority in the attorney general, who generally exercises it through the Drug Enforcement Administration (DEA). The Department of Health and Human Services (HHS) evaluates the scientific and medical evidence, but the DEA makes the ultimate legal determination of whether a drug has a "currently accepted medical use" for scheduling purposes, as the Justice Department explained in a 2024 legal opinion. Schedule I, the most restrictive category, includes substances deemed to have a high potential for abuse and no currently accepted medical use. These restrictions impede research, while officials cite insufficient evidence of medical usefulness to justify continued restrictions.

Cohen's bill would transfer authority to assess medical usefulness and drug-related risks—and to make scheduling decisions—from law enforcement to HHS, where those judgments more rationally belong. Under the new system, controlled substances would receive two classifications: a Roman numeral, I through IV, reflecting risks associated with misuse, substance use disorder, and threats to public health; and a letter, A through E, reflecting therapeutic value.

A substance could therefore be classified as high risk while still recognized for substantial medical benefits. That reflects an everyday reality of medical practice. Fentanyl, for example, can cause fatal respiratory depression and remains an indispensable anesthetic and analgesic. A drug's dangers do not erase its benefits.

The bill would also replace the vague "potential for abuse" standard for adding substances to the schedules with a standard based on the potential to develop a substance use disorder, expressly excluding isolated or occasional nontherapeutic use. Taking a substance for pleasure would no longer, by itself, satisfy that threshold.

Among the proposal's most consequential provisions is a requirement that officials consider whether scheduling a substance would itself threaten public health, including by encouraging people to substitute other drugs. They must also consider whether people use a substance to help control problematic use of another scheduled drug, as well as the harms associated with that other drug.

That would force federal officials to confront consequences that drug warriors routinely ignore. Banning a substance does not eliminate demand. Consumers may turn to underground suppliers, face uncertain potency and contamination, or switch to more dangerous products. Making a particular drug harder to obtain can leave its users worse off.

These requirements could be critical in disputes over kratom and its alkaloids, such as 7-hydroxymitragynine (7-OH), which some consumers report using for pain or to reduce their use of other opioids. Such reports should be part of an honest assessment of what consumers stand to lose when the government closes a legal supply channel.

An expert committee would evaluate each substance and publish its evidence and reasoning, making scheduling decisions more transparent and easier to challenge.

HHS would also assume from the DEA responsibility for registering researchers who study controlled substances. Qualifying researchers would gain an expedited registration pathway, with faster decisions for eligible small preclinical pilot studies. Federal officials currently demand evidence that these drugs have medical benefits while imposing restrictions that make it harder for researchers to obtain the drugs and conduct the studies needed to generate that evidence.

Cohen would require officials to reconsider existing classifications, setting a two-year deadline for 32 named substances and an eight-year deadline for most others. If officials miss those deadlines, statutory fallback classifications would apply.

The bill would also repeal the legal obligation of the director of the Office of National Drug Control Policy, the "drug czar," to oppose specified legalization efforts—a remarkable requirement for an office supposedly focused on evaluating drug policy.

Marijuana and tetrahydrocannabinols (THCs) would come off the controlled substance schedules altogether. The bill expressly makes that change retroactive, extending it to past offenses, pending cases, convictions, and juvenile adjudications.

Its sentencing reforms also merit praise. The proposal would remove the quantity-based trafficking provisions that impose five- and 10-year mandatory minimums and eliminate specified mandatory penalties when death or serious injury results. The bill would also limit certain repeat-offender sentencing enhancements to prior convictions that meet the narrower definition of a "serious drug felony." Among other requirements, the person must have served more than a year in prison and been released within 15 years of the new offense. Eligible prisoners could receive reduced sentences, and the Bureau of Prisons would be required to identify them, notify them, and file motions on their behalf.

These changes could spare people years of imprisonment. They deserve support even from those of us who would go much further.

The shortcomings remain significant.

First, the bill preserves criminal penalties for peaceful conduct involving drugs that remain controlled. It leaves the general federal simple-possession statute intact, including mandatory minimum jail terms for repeat offenses. Congress would continue to authorize imprisonment for possessing a substance without government permission.

Second, transferring power to HHS offers no guarantee against political interference. The secretary would appoint the expert committee in consultation with the drug czar. Its required membership emphasizes addiction medicine, toxicology, and substance-use services, without expressly reserving seats for pain patients, ordinary consumers, or civil liberties advocates.

The bill would allow emergency scheduling to bypass the new expert committee's review. It would also retain features of the current system: Temporary restrictions could last two years, with a possible one-year extension, and the statute would expressly exclude those orders from judicial review.

The bill would also transfer production quotas to HHS rather than abolish them. As I have argued before, presuming to know how much of each opioid more than 320 million Americans will need in the coming year exemplifies what economist Friedrich Hayek called the "fatal conceit." These quotas have contributed to shortages of injectable opioids in hospitals, jeopardizing care for surgical patients and those on ventilators. Transferring that power to a health agency does not solve the underlying knowledge problem. Congress should abolish the quotas.

The proposal substantially increases many maximum fines even as it reduces mandatory prison penalties. For an individual convicted of Schedule I or II trafficking without a qualifying prior conviction, the fine ceiling would rise from $1 million to $10 million. Congress should question this punitive expansion.

Finally, marijuana descheduling would leave Food and Drug Administration (FDA) authority intact. The bill expressly preserves the agency's powers under federal food and drug law, allowing it to regulate cannabis products that qualify as drugs, foods, or other products within its jurisdiction. It provides no explicit protection for a recreational cannabis market from FDA restrictions.

Those weaknesses warrant amendments. Scientific evidence can help people understand risks, but it cannot, by itself, justify depriving competent adults of the freedom to decide which risks they will accept. Autonomous adults should remain free to make informed choices about what they put into their bodies.

Cohen, who is retiring from Congress at the end of his term, is unlikely to see this sweeping reform pass during the brief post-election lame duck session. But his proposal can serve as a benchmark for reforming the Controlled Substances Act in the next Congress. Providing his successors with a framework that places greater weight on scientific evidence, recognizes the harms of prohibition, and reduces unjust punishment would leave Cohen with a substantial drug policy reform legacy.

The post Rep. Steve Cohen Thinks the DEA Shouldn't Be Practicing Medicine appeared first on Reason Magazine.

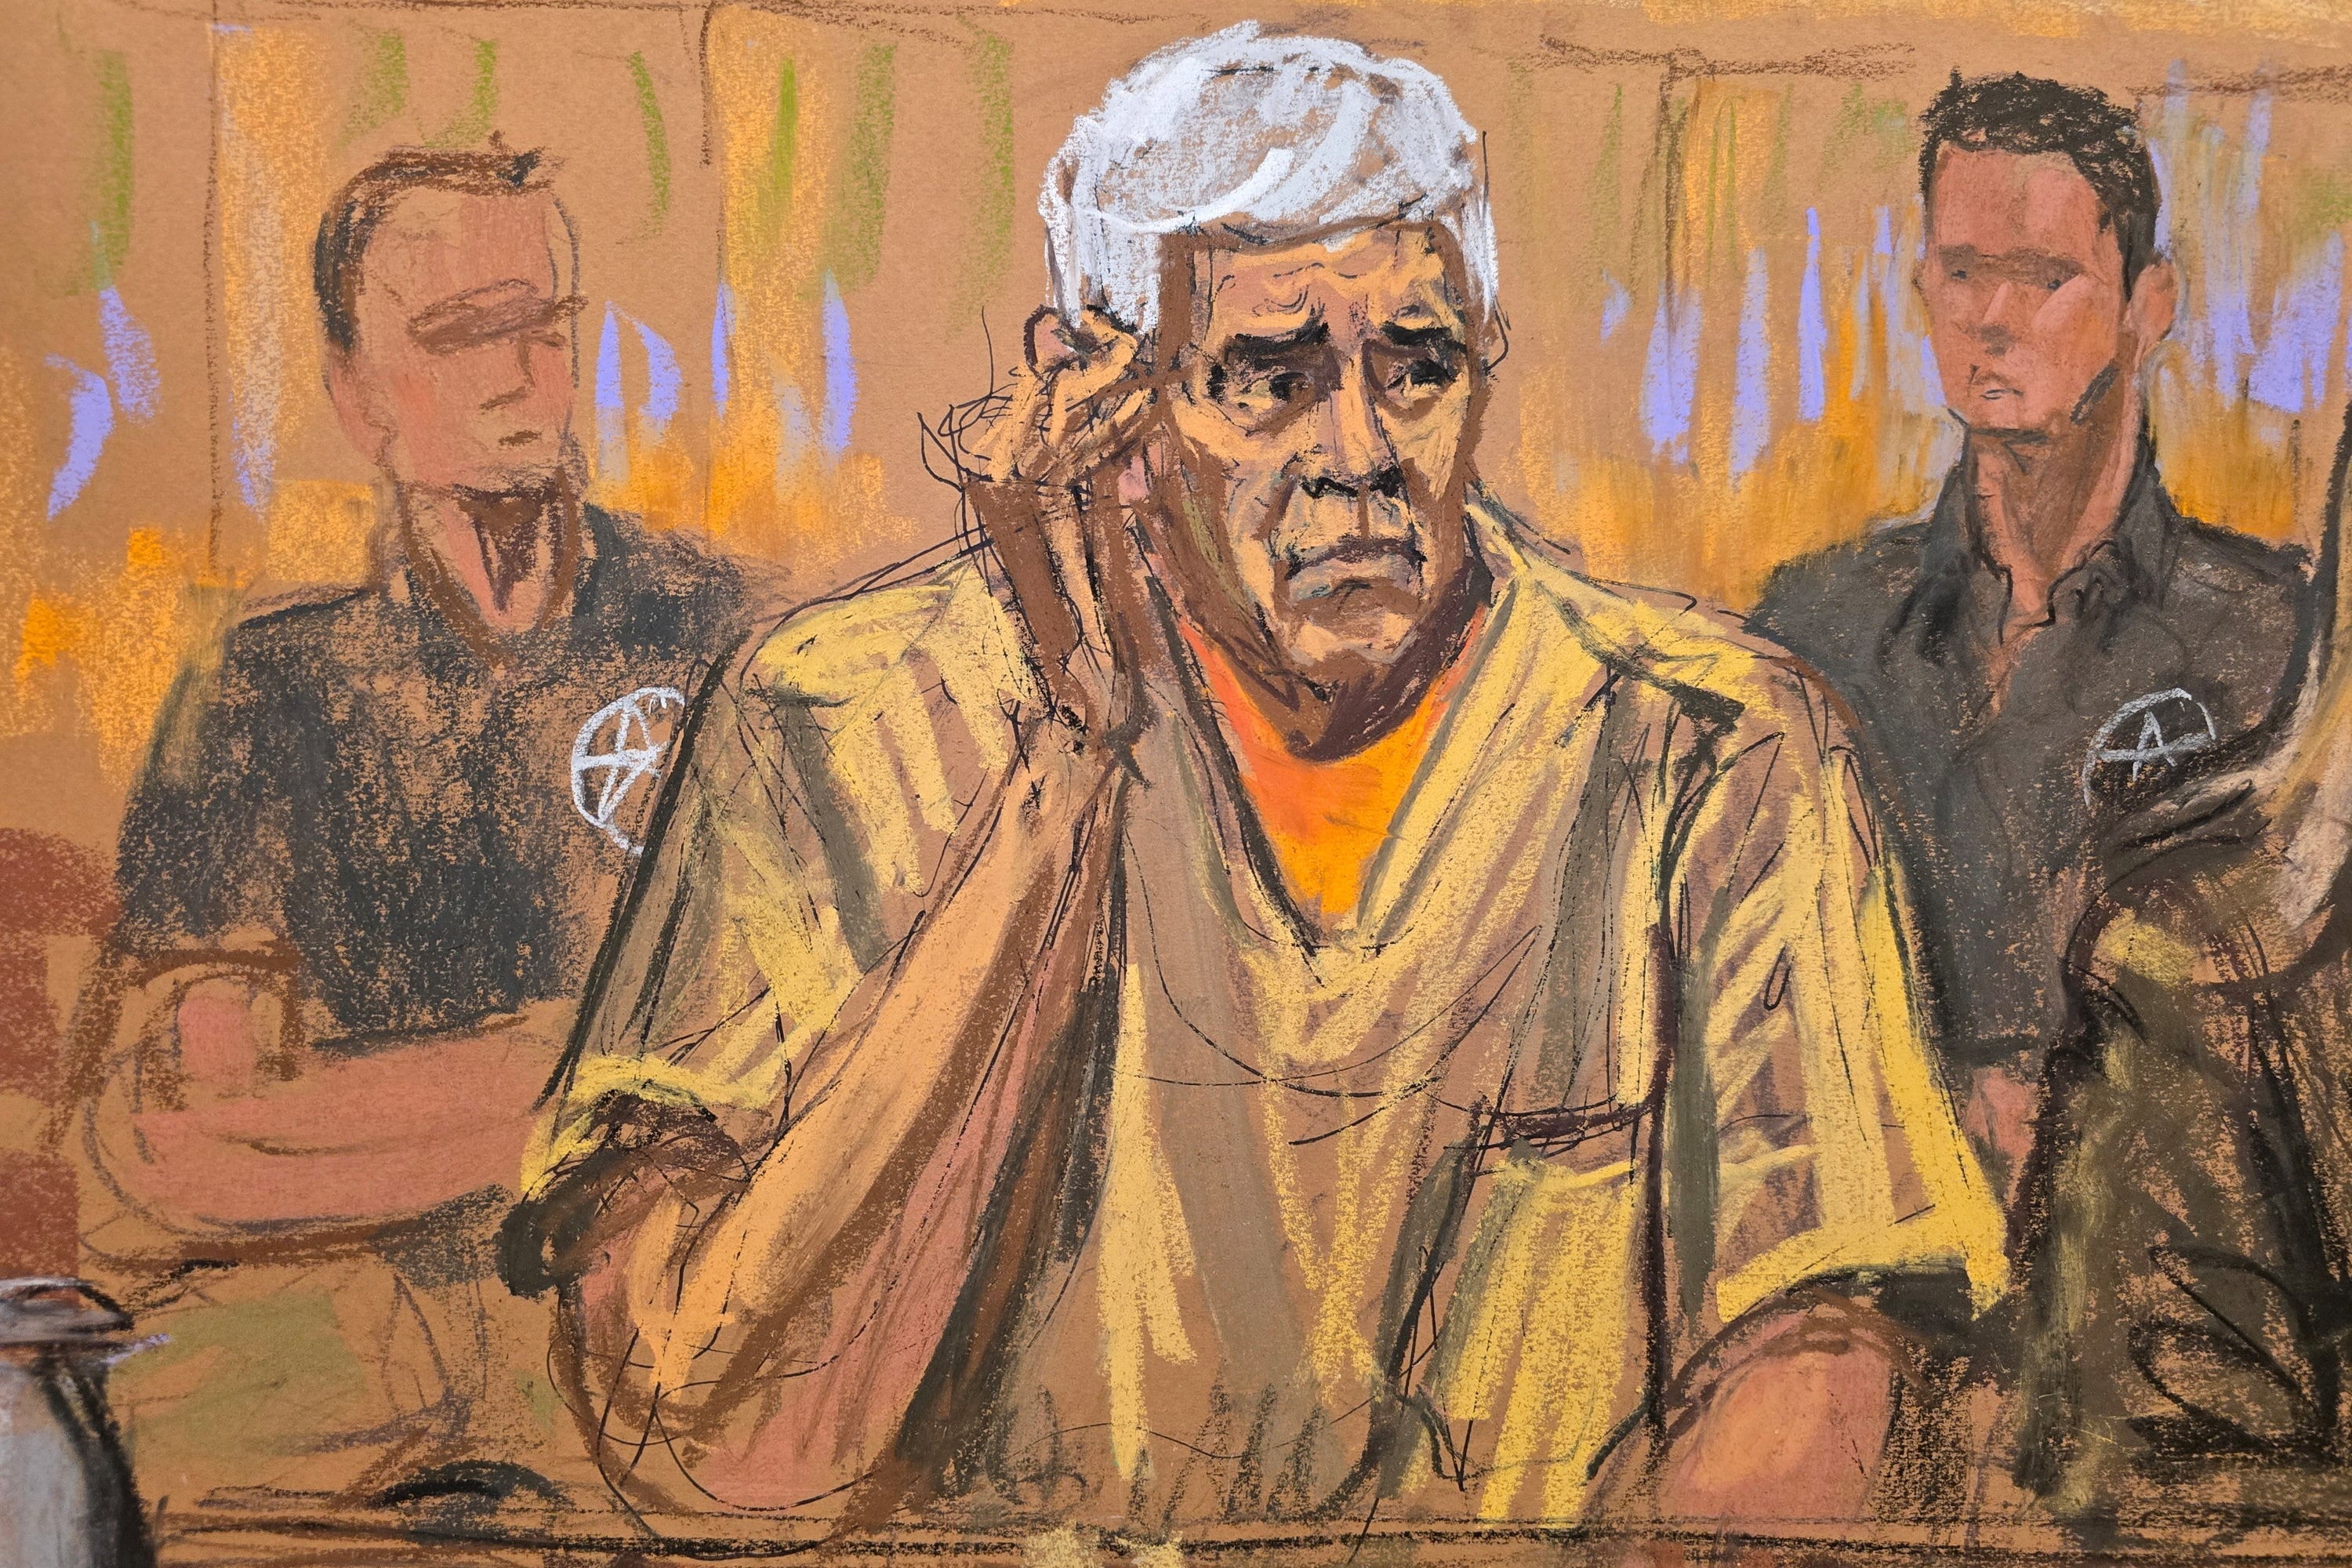
  •  

Caro Quintero: The legendary drug lord with whom the US will ultimately strike a deal

The United States Drug Enforcement Administration (DEA) neither forgets nor forgives. On its official website it hosts a microsite called “Justice for Kiki” dedicated to agent Enrique Camarena, who was killed in Guadalajara in February 1985. In the welcome message for the memorial, the DEA names Rafael Caro Quintero as the principal perpetrator of the kidnapping, torture and murder of its most famous agent, describing him as “a cartel kingpin who unleashed violence, destruction, and death.” The “Narco of narcos” is back in the headlines as he negotiates a deal that could lead him to plead guilty for events that took place 41 years ago. The story of this drug trafficker — one of the founders of the powerful Guadalajara Cartel in the 1980s — could end with an image far removed from the terrifying legend that surrounds Mexican kingpins of that era: a 74-year-old, battered man with a head full of gray hair, asking forgiveness for his sins before a jury in the U.S. Federal Court in Brooklyn.

Seguir leyendo

© Jane Rosenberg (REUTERS)

Courtroom sketch of Rafael Caro Quintero’s hearing in New York on October 14.
  •  

How Helping Someone Buy Drugs Can Send You to Prison for 20 Years

Scott Hancock | Joshua Greene/hancockonaddiction.org

Eight years ago, Scott Hancock, then 28, helped a 19-year-old acquaintance, identified in court records as T.G., buy fentanyl. At her request, Hancock, who had been addicted to opioids for years, got in touch with his drug dealer, who gave him five capsules that he handed over to T.G. in exchange for $20. Then Hancock gave the money to his dealer. Because T.G. subsequently died from a fentanyl overdose, Hancock is serving a 20-year sentence at a federal prison in Illinois.

That was the mandatory minimum sentence under 21 USC 241, which prescribes penalties for drug distribution resulting in death. Although that law has been on the books since 1986, the dramatic increase in fentanyl-related deaths during the last decade prompted a surge in federal drug prosecutions involving overdoses, which rose by 44 percent between FY 2019 and FY 2023. Hancock's case was part of that trend, and it prompted his mother, G.D. Hancock, a retired finance professor, to delve into the subject, resulting in a database that sheds light on what happens when the government treats accidental deaths as homicides.

So far, Hancock has identified 2,930 sentences in such cases since 2010. That includes 1,399 federal cases and 1,531 state cases, which rely either on laws dealing specifically with drug-induced deaths or on more general statutes addressing felony murder, "depraved heart" homicide, or manslaughter.

Sentences of 20 years or more were pretty common at the federal level, accounting for 37 percent of the cases, compared to 13 percent at the state level. The vast majority of the cases (84 percent) were resolved by plea deals. That is not surprising, given the potential consequences of going to trial. While the median sentence for defendants who pleaded guilty was nine years, it was 20 years for defendants who insisted on making the government prove its case.

Hancock's tally is based on news reports, court records, announcements by state and federal prosecutors, her own "case files and research," and "cases sent in by families, lawyers and researchers." A separate database compiled by researchers at Northeastern University, drawn from news reports, includes 3,264 cases involving drug-induced homicide from 2011 to 2022.

These prosecutions are morally nonsensical. They treat people who voluntarily consume drugs as helpless victims of supposed predators who gave them the drugs they wanted. By similar logic, bartenders and liquor store owners should be held criminally liable whenever a customer succumbs to alcohol poisoning or the long-term effects of heavy drinking. The main difference is the legal status of the drug, which is arbitrary, politically determined, and historically contingent. And while illegal drugs pose special hazards, that is a result of prohibition, which creates a black market where product composition is highly variable and unpredictable.

Charging people with homicide based on accidental overdoses would be illogical and unjust even if the defendants were limited to actual drug dealers. But you can be charged with drug-induced homicide even if your "trafficking" consisted of nothing more than sharing drugs with a relative, romantic partner, friend, or acquaintance. Based on the information Hancock was able to glean, she counts 241 cases where the person who died from an overdose was the defendant's friend, partner, or family member, and other sources suggest such prosecutions are common.

The Northeastern University researchers analyzed a sample of 213 online news reports from 2000 to 2017. They found that 50 percent of defendants charged with drug-induced homicide were caretakers, family members, friends, or partners of the people who died.

In 2021, when the Pittsburgh Tribune-Review examined Pennsylvania prosecutions for "drug delivery resulting in death" (DDRD), it described a case involving "a Westmoreland County man" who "died from an overdose of drugs he'd gotten from a friend of a friend of a friend." Although "the drugs ultimately came from a man called 'Bee' in Penn Hills," the paper noted, "the three individuals between the victim and Bee were all charged" with DDRD, a first-degree felony punishable by up to 40 years in prison.

The Tribune-Review described several other DDRD defendants, including "a Delmont woman" who "called paramedics when she found her boyfriend unresponsive in their bathroom"; "two friends" who bought heroin for a man who overdosed at a Taco Bell; and "a Monessen woman" who "sent her cousin to buy a brick of heroin" and "sold five stamp bags to a friend, who then sold four bags to an Elizabeth Borough man who died from a fatal overdose."

The Tribune-Review also found that "many facing these charges are relatively low-level dealers." Jonathan Fodi, a defense attorney and former prosecutor, told the paper he and his colleagues had never seen a DDRD case involving a high-level dealer. Given the need to prove a link between the defendant and the person who died, that is not surprising. But that situation compounds the injustice of treating such deaths as homicides, since low-level dealers often do not know exactly what is in the drugs they are selling.

A 2002 analysis of 32 drug-induced homicide prosecutions, published in the New Jersey Law Journal, found that "25 involved prosecution of friends of the decedent who did not sell drugs in any significant manner." According to a 2017 report by a Wisconsin TV station that looked at the 100 most recent prosecutions for drug-induced homicide in that state, "nearly 90% of those charged were friends or relatives of the person who died, or the lowest people in the drug supply chain." When the Chicago Tribune examined drug-induced homicide cases filed between 2011 and 2014, it found "the defendant was typically the last person who was with the person who overdosed."

Even people who support the war on drugs should be able to recognize the injustice of sending people to prison for 10 or 20 years based on their tangential roles in deaths they neither caused nor intended. And far from making such deaths less likely, that policy impedes potentially lifesaving medical assistance because the risk of a homicide charge is apt to discourage bystanders from calling for help. That daunting deterrent undermines the goal of "Good Samaritan" laws that are supposed to shield 911 callers from criminal charges in such situations.

The official justification for these prosecutions is completely disconnected from the reality of the cases. "Deaths from illicit drugs, especially fentanyl, are at historic highs," the Drug Enforcement Administration (DEA) said in a 2023 press release. Because the DEA is "committed to protecting Americans and saving lives by pursuing those responsible," the agency explained, it aims to "make sure as many drug traffickers involved in those deaths as possible get an appearance in front of a judge."

As an example of that strategy, the DEA cited Scott Hancock's case, describing him as a "trafficker" who was "found guilty of providing the drugs that killed a 19-year-old woman in 2018." Given the details of that transaction, it is hard to see the logic here. Sending someone like Hancock to prison for 20 years has nothing to do with "saving lives."

The post How Helping Someone Buy Drugs Can Send You to Prison for 20 Years appeared first on Reason Magazine.

  •  

The DEA Wants To Turn 7-OH Consumers Into Criminals

Kratam-2-science-products | Puntasit Choksawatdikorn/Dreamstime

The federal drug police want to turn consumers of certain concentrated kratom-derived products into criminals while leaving traditional kratom leaf products outside the ban. Before exposing adults to arrest and prosecution, the feds owe them a scientific explanation for that distinction.

On October 14, the Drug Enforcement Administration (DEA) announced its intent to temporarily place 7-hydroxymitragynine (commonly called 7-OH) and mitragynine pseudoindoxyl—above specified thresholds—in Schedule I. Schedule I is the category for drugs that the agency thinks have "no currently accepted medical use" and "a high potential for abuse." A scheduling order could be issued on or after November 13.

The DEA already classifies mitragynine pseudoindoxyl as a Schedule I substance regardless of concentration. The proposal would ease that restriction by introducing thresholds—while imposing new Schedule I restrictions on 7-OH under the same criteria.

The Food and Drug Administration (FDA) and the Department of Health and Human Services (HHS) have supported the DEA's move, and HHS supplied the proposed thresholds. Under the temporary scheduling provision of the Controlled Substances Act, the DEA must consider HHS's comments but need not follow its recommendations. Congress gave a law-enforcement agency the authority to decide which drugs individuals may consume.

The ordinary scheduling process gives health officials more authority: HHS's scientific and medical findings bind the DEA, and its recommendation against control prevents the agency from proceeding. But temporary scheduling lets the DEA bypass those requirements when it determines a substance poses an imminent hazard to public safety.

Congress should never have given federal drug police that power. Having done so, it should at least demand compelling evidence before they exercise it.

Kratom comes from a Southeast Asian plant whose principal alkaloid is mitragynine. Its leaves contain trace amounts of 7-OH. Manufacturers also sell concentrated 7-OH products and products containing the related compound, mitragynine pseudoindoxyl.

Millions of Americans use kratom or kratom-derived products. A 2022 review cited an estimate of 2.1 million U.S. users in 2020. In a survey of 2,798 users, 91 percent reported using it for pain and 41 percent said they use it to reduce or stop opioid use. In a letter to HHS, nine military veterans described using 7-OH to manage pain and symptoms of post-traumatic stress disorder and to move away from other opioids and from alcohol. They warned that banning it could drive them back to more dangerous drugs.

These reports describe benefits that warrant further study and needs that will persist after a ban.

Concentrated 7-OH products deliver a potent alkaloid without requiring consumers to ingest large amounts of kratom leaf. 7-OH is significantly more potent than mitragynine in activating the opioid receptors involved in pain relief. Researchers still need to determine how its benefits and risks compare across different human doses.

The DEA's proposed criminal controls hinge on concentration and composition. The concentration threshold is 1 milligram per gram of solid material or 1 milligram per milliliter of liquid, calculated for the two covered substances combined. Products would also trigger controls if the mitragynine-to-covered-substances ratio fell below 100 to 1.

Consider a tablet containing 15 milligrams of 7-OH, a strength advertised by some sellers. If the tablet weighs one gram, its concentration exceeds the limit fifteenfold. Diluting the same 15 milligrams into a product weighing 15 grams brings it to the concentration limit. Consuming the entire product still delivers the same dose. It would also need at least 1,500 milligrams of mitragynine to avoid the separate ratio restriction.

Adding bulk changes the concentration but does not change the amount of 7-OH consumed. These calculations tell us nothing about whether that dose is effective or safe.

The DEA acknowledges that controlled trials have not established safe consumption limits or standardized dosing for concentrated 7-OH products. Neither DEA nor HHS has determined that below-threshold products are safe.

In a public comment submitted to HHS in July, I urged officials to obtain the human evidence needed to justify a threshold before setting one. Animal studies can reveal hazards, including dependence and respiratory depression, but they cannot, by themselves, identify a scientifically defensible cutoff for human consumption.

Officials may intend these thresholds to distinguish traditional kratom from concentrated products. What evidence shows that crossing that boundary justifies criminal penalties? 

The DEA also owes consumers an accounting of what prohibition could do to them. People seeking relief from pain or withdrawal will still need it after a ban. Some may abandon these products, while others may turn to illicit sellers or switch to other opioids. Criminalizing those choices could make them more dangerous.

Misleading labels, contamination, dependence, and drug interactions warrant attention. Accurate labeling, independent testing, age restrictions, and enforcement against fraud can address several of these concerns. Before resorting to criminal penalties, the DEA should explain why those measures would be inadequate.

We already know how difficult it is to verify a drug's identity, strength, and purity in an illicit market. Creating another prohibited product will give that market another opportunity.

Autonomous adults should be free to decide which substances they consume and which risks they accept. The DEA proposes taking that choice away even as it acknowledges major gaps in the medical evidence. Before the drug police turn more consumers into criminals, they should at least demonstrate how doing so will make those consumers safer.

The post The DEA Wants To Turn 7-OH Consumers Into Criminals appeared first on Reason Magazine.

  •  

How California became the birthplace and refuge for the children of Mexico’s most feared narcos

In July 2011, a 22-year-old woman arrived at the Calexico checkpoint on the Mexico–California border carrying a U.S. passport with a navy-blue cover. Her eight-month pregnancy and Sinaloa accent were hard to hide. A customs agent asked routine questions: where she had come from, where she was headed, and what she was carrying. Despite her answers and the document she presented, he sent her for a secondary, more thorough inspection. Other federal officers meticulously searched her belongings and the contents of her cellphones. Minutes later, once the rigorous procedure was complete, they allowed her into the country.

Seguir leyendo

© Mary Altaffer (AP)

Emma Coronel leaves a New York courthouse with her daughters, June 2018.
  •  

Un anillo de cobre encontrado en Herodión con el nombre de Pilato pertenecía a un trabajador de su administración en Judea

El hallazgo arqueológico no podía ser más modesto: un pequeño anillo de aleación de cobre, con unas pocas letras griegas grabadas y la imagen de una vasija de cerámica. Sin embargo, su apariencia insignificante oculta una historia extraordinaria que ha mantenido en vilo a los especialistas desde que su existencia fue revelada en 2018. El […]

  •  
❌